

Prof Joseph Sabbagh presents a clinical case study featuring an upper-molar root canal treatment using GenENDO Revo-S+ files and BioRoot Flow bioceramic sealer.
Root canal treatment (RCT) is a common endodontic procedure aiming to preserve a tooth through proper cleaning, shaping and obturation of the root canal system. When properly performed, root canal treatment has an estimated success rate of 90.3% (Ricucci et al., 2011). For retreatments, the success rate is between 65.5% and 77.6% (Stueland H et al., 2023).
Recent innovations in endodontics are revolutionising root canal therapy by integrating advanced imaging, precision instruments and enhanced disinfection methods, making the treatment easier and more predictable. Three-dimensional imaging – particularly cone-beam computed tomography (CBCT) – enables detailed visualisation of complex canal morphologies and guided access.
Cleaning and shaping of a root canal system relies on using flexible nickel-titanium (NiTi) files, simplified sequences, and improved alloys, together with apex locators and enhanced rotary motors, to facilitate efficient shaping of curved canals while minimising procedural errors. This enables subsequent steps, including coronal flaring, creating a reproducible glide path, determining the working length, and carrying out biomechanical preparation and disinfection of the root canal system.
Ultimately, the procedure aims to achieve effective obturation, ensure the longevity of the restoration, and preserve as much of the natural tooth structure as possible (Elmatary et al., 2025; ESE, 2006).
What makes an adequate endodontic treatment?
The dental community has understood that an adequate endodontic treatment does not mean enlargement of the canals, but rather a proper disinfection of the root canal system combined with a three-dimensional seal. Several techniques using gutta percha, delivered in different modes, are used for the obturation phase. For several years, the warm vertical technique, described by Schilder in 1972, was considered the gold standard in endodontics. Although showing good clinical outcomes, this technique is complex and involves several steps. Recent development in biomaterials has led to a new category of products called bioceramics, based mostly on calcium silicate (CSCs). They can be used as cements in restorative dentistry for pulp vitality preservation, or as sealers in endodontics (Dong and Xu, 2023).
During the obturation step, the use of bioceramic sealer combined with a single gutta percha cone makes this phase easier and more predictable.
The following clinical case report details a root canal treatment of an upper molar. The root canal preparation was completed with two NiTi files in continuous rotation (Revo-S+, GenENDO, Septodont). The obturation was done using a recent bioceramic sealer (BioRoot Flow, Septodont).
Case presentation
Clinical signs and symptoms
A 59-year-old male patient presented to the dental clinic to complete a root canal treatment after severe spontaneous pain localised at the upper right posterior quadrant. The pain had persisted for five days and intensified with hot stimuli. Consequently, the patient went to a hospital offering an emergency dental service. They created an access cavity in tooth number 17 to relieve the pain, placed a temporary restoration, and asked him to continue the treatment with an endodontist.
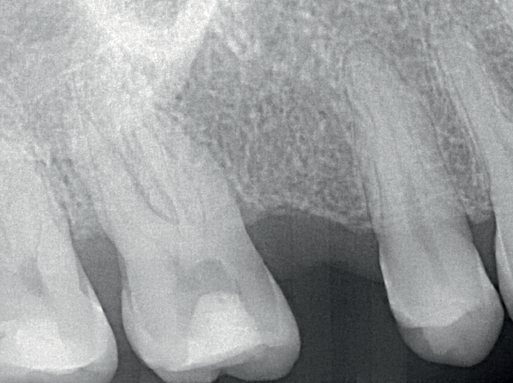
A preoperative periapical radiograph revealed an apical lesion on the palatal root of tooth 17 (upper right second molar) (Fig. 1) with a widened periodontal ligament space around the mesial root. No swelling or sinus tract was visible.
Diagnosis
Based on the patient’s explanations, clinical and radiographic findings, the tooth was diagnosed with a necrosis following an acute irreversible pulpitis. A non-surgical root canal treatment was planned to complete the emergency procedure initiated at the hospital.
Procedure and treatment
Following administration of local anaesthesia (Septanest, 1:200,000, Septodont, Saint-Maur-des-Fossés, France), the temporary cement was removed using a diamond bur and a carbide tungsten bur was used to finalise the access cavity. Three canal orifices were identified: mesiobuccal (MB), distobuccal (DB) and palatal (P). The working field was isolated using a latex rubber dam fixed with a Softclamp (Kerr, Orange, USA) to avoid any gingival fluid contamination or accidental instrument swallowing.
Canal preparation
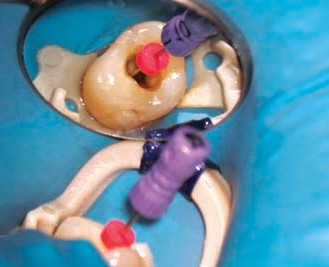
A manual stainless steel 010 K-File (GenENDO, Septodont) was used to scout the canals’ patency (Fig. 2). Final working length was determined using an apex locator and confirmed radiographically.
Cleaning and shaping were initiated using a crown-down technique with rotary files GenENDO Revo-S+ (Septodont) SC2 and SU. There was no need for coronal flaring due to the size and the straight form of the canals.
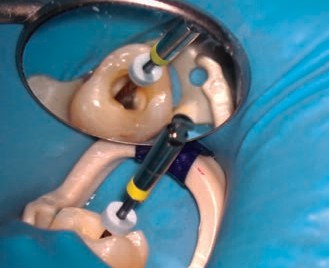
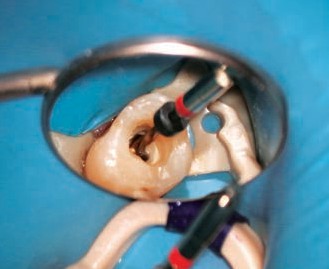
The shaping of the canal was done with two NiTi Files: GenENDO Revo-S+ SC2 (25/0.4 symmetrical design) was used first, centred downward on the canal in two or three motions. Once the length was obtained with the SC2, a final shaping was done with the GenENDO Revo-S+ SU (25/.06 asymmetric design) for a uniform taper and optimal preparation (Fig. 4) following one centred downward and one upward movement with selective wall support, finishing at working length.
Obturation
Copious irrigation with 3.5% sodium hypochlorite was performed throughout instrumentation, and canals were irrigated with EDTA on a final flush flow to remove the smear layer. Rechecking of canal patency was regularly ensured using a GenENDO K-File 010 between each instrument. The access cavity with the three cleaned and prepared canals is shown (Fig. 5).
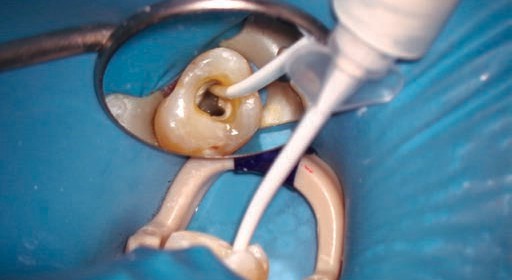
In the absence of swelling and after complete drying of the canals, contemporary endodontic strategies recommend the obturation of the canal system during the same session. After final irrigation, the canals were dried using one or two paper points to avoid over-drying. BioRoot Flow (Septodont), a recently introduced bioceramic sealer, was injected into each canal with low pressure (Fig. 6).
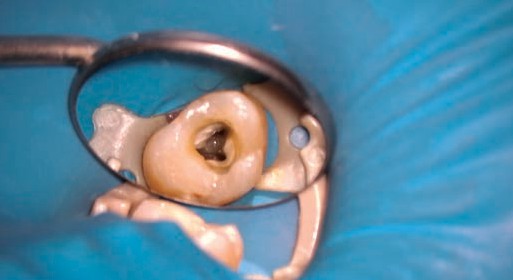
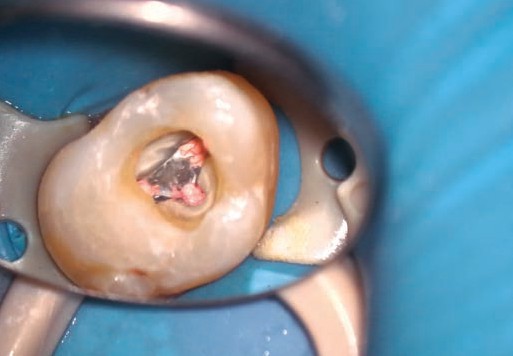
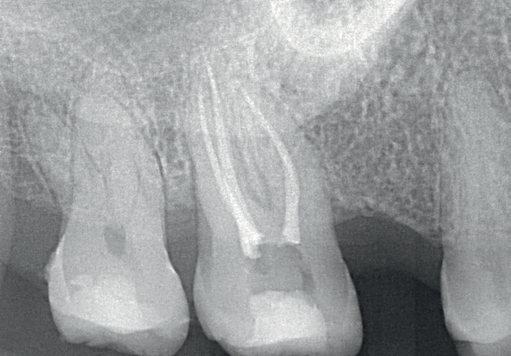
Using a single-cone technique, one master cone of gutta percha, previously calibrated and confirmed radiographically, was inserted into each of the canals. The gutta percha points were then cut using a heat-cutting device and compacted with an endo plugger. The canal entrances after obturation and compaction are shown (Fig. 7). A Teflon pellet was placed in the access cavity and covered by a temporary cement. The postoperative radiograph shows the canal system properly shaped, cleaned and homogenously filled to the radiographic apex (Fig. 8).
Follow-up and outcome
At the one-month follow-up, the patient reported no pain or discomfort. Clinical testing showed no tenderness, and radiographic examination revealed resolution of the periodontal ligament widening and signs of periapical healing. The tooth remained functional and symptom-free.
Discussion
Endodontic treatment of molars can be challenging due to variations and complexities in root canal morphology. Use of magnification, electronic apex location, and simplified rotary instrumentation enhanced the precision of canal shaping. The obturation phase was performed with a bioceramic sealer and a single gutta percha cone, which is being used more and more in endodontics.
Successful root canal treatment depends on adequate diagnosis, canal disinfection, and hermetic obturation. Early intervention prevented the progression of periapical disease and preserved the natural tooth structure, avoiding extraction.
Conclusion
This case highlights the importance of comprehensive diagnostic and clinical protocols in the endodontic treatment of maxillary molars. With proper technique and patient compliance, even complex molars can be predictably treated, resulting in long-term tooth retention and functional restoration.
References
- Ricucci D, Rutberg M et al. 2011. A prospective cohort study of endodontic treatments of 1,369 root canals: results after 5 years. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 112(6): 825-42.
- Stueland H, Ørstavik D, Handal T. 2023. Treatment outcome of surgical and non-surgical endodontic retreatment of teeth with apical periodontitis. Int Endod J. 56(6): 686-696.
- Elmatary A, Moawad E, Heidarifar O et al. 2025. Endodontic access cavity preparation: challenges and recent advancements. Br Dent J 238, 469–475.
- Dong X and Xu X. 2023. Bioceramics in Endodontics: updates and future perspectives. Bioengineering 10, 354.
Disclaimer
The views, opinions, and statements expressed in this content are solely those of Dr Joseph Sabbagh.
Dr Joseph Sabbagh is solely responsible for the scientific and medical positions presented. The pictures and radiographs used in this case study are the property of Dr Joseph Sabbagh.
The author reports a professional and/or financial relationship with Septodont relevant to this article.
The products referenced in this case study are medical devices. BioRoot Flow is available in the United States and the European Union and complies with applicable regulatory requirements (FDA 510(k) or MDR 2017/745). GenENDO Range complies with the applicable requirements of the European Union (MDR 2017/745) and is available in EU only.
Please read the instructions for use carefully before use, paying particular attention to warnings, precautions, and contraindications. These medical devices are regulated health products. Communication intended for healthcare professionals only.
This article is sponsored by Septodont.


